Platform Company Versus Formulation CRO in Peptide Delivery and Why the Business Model Difference Matters to GLP-1 Investors
Platform ownership of delivery technology captures more value than formulation contracts do.

In peptide delivery, a platform company owns proprietary technology that can build value through use with more than one molecule and indication, while a formulation CRO sells services under contracts that must be renewed. For GLP-1 investors, that distinction separates ownership of reusable delivery IP from exposure to formulation work. Better delivery may expand what established medicines can do, but the business model determines who captures that value.
Why GLP-1 investors are increasingly evaluating delivery platforms, not just molecules
The dominant GLP-1 molecules are established, so the investment question increasingly concerns who owns the infrastructure to deliver them better. Rather than engineering entirely new molecular entities, companies are investigating technologies that change how existing medicines are absorbed, distributed, and tolerated. A molecule with known biology can support different development opportunities if a new route changes where it reaches or how patients experience treatment.
A majority of injectable GLP-1 patients discontinue within a year, and a large share abandon prescriptions before a single fill. Amgen pointed to data showing that 58% of patients who stop regain weight within 12 months. Those findings expose a gap between a medicine’s efficacy and the durability of its use. They make sustained treatment both an investment question and a prescribing concern.
That question also changes the unit of analysis. With escalating R&D costs and extended regulatory timelines, investors have reason to examine whether a company’s technology can support several programs and reduce dependence on one candidate. Can the same delivery system work with another peptide or indication? If so, the investment may encompass a reusable technological base. If not, the delivery story may still be promising, but its economics remain tied to a narrower asset.
What the subcutaneous route cannot do, and why that gap is an investment signal
Subcutaneous GLP-1 receptor agonists generate high systemic exposure but achieve limited direct brain penetration. That creates a distribution problem. Exposure throughout the body is not equivalent to exposure at the neuronal populations relevant to a neurological indication, and systemic exposure also brings tolerability concerns. The blood–brain barrier, or BBB, therefore helps define which opportunities a delivery route can plausibly address.
GLP-1 receptor agonists are associated with reduced risks of seizures, addiction, and neurocognitive disorders including Alzheimer’s and dementia. Preclinical models also show modulation of mesolimbic dopamine signaling and attenuation of the reinforcing effects of addictive substances. Yet association and preclinical activity do not establish clinical efficacy. The case for investing depends on whether enough of the drug can reach the brain tissue where it needs to act.
The phase 3 EVOKE and EVOKE+ trials sharpen that distinction. These trials of oral semaglutide in Alzheimer’s patients did not meet their primary endpoint on the CDR-SB scale at week 104, despite epidemiological associations with reduced dementia incidence. They tested oral treatment in place of subcutaneous delivery. Their failure does not isolate route as the cause or prove that direct brain delivery would succeed. It does, however, strengthen the case for examining CNS exposure rather than assuming that an established molecule and encouraging cohort data are enough.
For investors, the unresolved question is specific. Could a different route produce therapeutically useful brain exposure without relying on high systemic exposure? Addiction and dementia represent potential extensions of GLP-1 biology, but their value remains conditional on demonstrating that delivery and clinical response can be connected.
How the nose-to-brain route works and why nanoparticles are the enabling layer
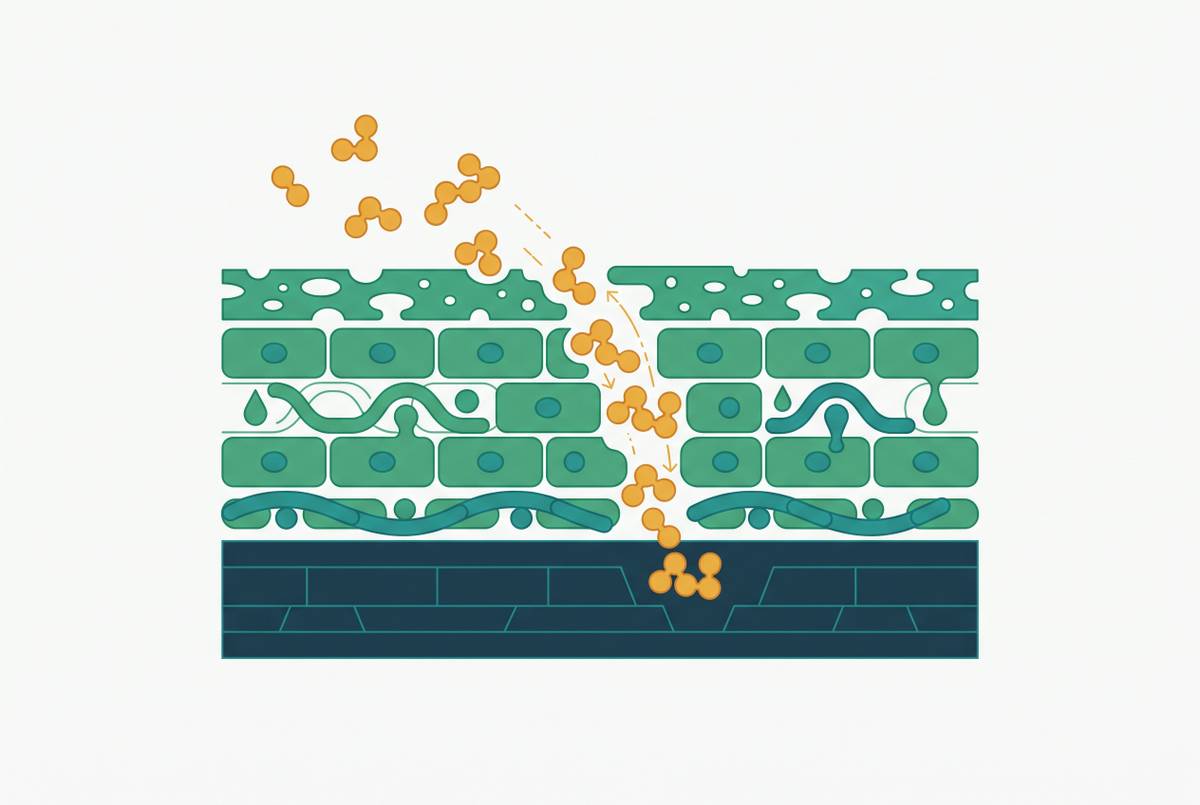
The nasal route offers access to the CNS through the olfactory and trigeminal pathways, which connect the nasal mucosa to the brain. These are cranial nerve I and cranial nerve V. Transport through these pathways can bypass the BBB and hepatic first-pass metabolism, making nose-to-brain delivery a different architecture rather than simply another way to administer a systemic drug. A formulation must be able to use that access reliably.
Akita et al.’s 2021 study found that a GLP-2 derivative reached the trigeminal sensory nucleus rapidly after intranasal dosing in mice. Winterdahl et al.’s 2025 first-in-human PET study using labeled oxytocin showed that intranasally administered peptides reached human brain tissue, with detectable uptake within tens of minutes. These findings establish useful steps in the argument. They do not make different peptides interchangeable or establish therapeutic efficacy for intranasal GLP-1 treatment.
Human anatomy is a substantial translational constraint. In rodents, olfactory epithelium covers roughly half of the nasal surface area, compared with less than ten percent in humans. Mucociliary clearance also clears away most of the material deposited in the nose within minutes. An unprotected peptide therefore has a short absorption window, and strong rodent results cannot simply be projected onto human dosing.
Nanocarriers are engineered to address those constraints. Polymeric nanoparticles can hold active principles in their core, have a high surface-to-volume ratio, and keep releasing them locally while slowing how quickly they are cleared. Mucoadhesive systems extend retention, while permeation enhancers improve mucosal crossing.
Long-term nanoparticle accumulation, chronic toxicity, immunogenicity, complement activation, and off-target organ deposition are poorly understood. Advanced human BBB models and microfluidic BBB-on-chip systems are recommended to improve translational predictability. For investors, proprietary nanoparticle IP is valuable precisely because these barriers are difficult to solve. Patent ownership alone does not establish that they have been solved.
The structural difference between a platform company and a formulation CRO
A platform company owns a technological base that it licenses or applies across products and indications. A formulation contract research organization, or CRO, performs services for clients. The distinction concerns what the company sells. In the first case, successive applications can build the value of proprietary delivery IP. In the second, revenue comes from doing formulation work under one contract after another.
Asset-centric and platform-centric biotechnology differ in ways that overlap with this distinction without matching it exactly. An asset-centric company follows a concentrated path built around one goal, one asset, and one exit. A platform-centric company seeks to build value by using its technology in more than one application. A CRO sells services instead of following either of those development paths, which may bring steadier cash flows with less risk, though it has long been seen as a business with lower margins.
No one business model is best in every setting. Investors can go wrong by paying for one kind of business while buying another. Does a new peptide application deepen the value of technology the company controls, or does it mainly create another contract to execute? That question is more revealing than the word “platform” in a presentation.
Stronger platforms can turn reusable technology into standardized products, repeatable services, higher utilization, or falling unit costs. Without that conversion, scientific breadth may remain commercially awkward. Delivery-specific patents, use across molecules, licensing activity, and a technology-led rather than lead-asset-led business description provide evidence of platform structure, but no single feature settles the question.
What the data shows about platform company survival and deal value versus non-platform companies
When a lead program fails, it tests how much value is left in the business. If the company’s technology can work beyond that program, it may still have another use. The lower failure rate among platform companies is consistent with that structural advantage, although it does not guarantee resilience for any particular platform.
The same analysis found that a majority of platform companies had at least one licensing agreement, compared with well under half of non-platform companies. Platform companies also had a total potential deal value many times higher than the average for non-platform companies. Licensing gives reusable technology a financial expression. It allows the business to participate in programs beyond its own lead asset, provided partners see value in the underlying IP.
Potential deal value still needs careful interpretation. It is not the same as realized revenue, and an association between platform status and outcomes does not establish that the label caused them. Nor is a comparison of platform and non-platform biotech companies automatically a direct comparison with formulation CROs.
Delivery-platform companies showed the highest rate of lead-asset success in the analysis. The proposed explanation was that pairing established molecules with new delivery technology reduces development risk relative to combining a novel molecule with a novel mechanism. An intranasal GLP-1 platform fits that proposed archetype, with known receptor biology and a potentially extensible delivery system. Its remaining burden is to demonstrate that the new route works, safely, across the proposed applications.
How can investors distinguish real peptide delivery platform IP from positioning language?
For investor due diligence, the first question concerns patent architecture. Does the portfolio protect the delivery mechanism itself, including nanoparticle composition, surface modification chemistry, mucoadhesive system design, or device-formulation integration? Protection confined to a particular peptide combination supports a narrower claim. Breadth across molecules and indications is the relevant signal, because the investment thesis depends on reuse.
The next question concerns the scientific foundation. A publication record with independent citations can show that the underlying work has been evaluated by the broader research community. Academic origin is not sufficient by itself. A body of science that supports a reusable mechanism carries more weight than a prestigious affiliation used to back an untested business claim. Even work that is widely cited still needs evidence that it can translate to humans.
Pipeline and contract structure then test whether that foundation has business consequences. Has the same core technology been applied, or credibly mapped, to more than one molecule or therapeutic area? Do agreements license technology or set up technology-led co-development, or do they pay for formulation services? A pipeline confined to one peptide may function economically as an asset, regardless of its description. Fee-for-service revenue instead scales with the work, headcount, and equipment utilization required to deliver it.
Translational credibility supplies a further test. Published data should address rodent efficacy, nasal volume constraints of 5–6 cm³, mucociliary clearance, and the difference in olfactory coverage between rodents and humans. MetP Pharma’s 2025 preclinical data illustrates the type of evidence to examine, including brain-to-plasma ratios greater than 1, dose-proportional CNS exposure, and explicit comparisons with subcutaneous and oral benchmarks. Its positioning across a class of peptide drugs also makes extensibility a claim that can be scrutinized. These criteria distinguish a durable investment thesis from exposure to “platform” branding without platform economics.
Why the convergence of the EVOKE failure, the adherence crisis, and nanoparticle science makes this the right moment to apply the platform lens
Three developments now bring delivery ownership into sharper focus. The EVOKE failures cast doubt on the assumption that established GLP-1 biology will lead directly to efficacy in Alzheimer’s with the treatments now in use. Public persistence data exposes the limits of injectable treatment as a sustained commercial proposition. Meanwhile, nanoparticle-based intranasal research provides measurable exposure results.
Each development also tests a different part of the investment case. The neurological results raise questions about where a drug needs to go, while discontinuation raises questions about whether patients will remain on treatment. Preclinical brain-to-plasma ratios and human PET uptake address aspects of delivery feasibility. A careful assessment keeps these kinds of evidence separate. Otherwise, promising exposure data can be taken as proof of efficacy, tolerability, or persistence.
That separation is what makes the platform lens useful now. Patent depth identifies what the company controls, pipeline extensibility tests whether it can reuse that control, licensing structure shows how it seeks to monetize it, and translational rigor tests whether the science can support the business. A CRO can sell services that have value without owning the technology that brings those returns. The investment decision is therefore not whether “platform” sounds more attractive, but whether the price reflects a reusable proprietary system or a sequence of contracts.
Sources
- Intranasal drug delivery: Unlocking the nose-to-brain route for central nervous system therapies - ScienceDirect
- Nose-to-brain drug delivery: from bench to bedside
- Intranasal delivery of glucagon-like peptide-1 to the brain for obesity treatment: opportunities and challenges: Expert Opinion on Drug Delivery: Vol 21, No 7
- Navigating the Nose-to-Brain Route: A Systematic Review on Lipid-Based Nanocarriers for Central Nervous System Disorders
- Advancements in Nanocarrier Systems for Nose-to-Brain Drug Delivery
- 2025 American Academy of Neurology Abstract Website