Which Universities Hold the Deepest Peptide Nanoparticle Patent Portfolios and Why Columbia's Stands Apart
Columbia's peptide nanoparticle patents lack the documented foundation claimed for them.

University peptide nanoparticle patent depth is best judged by coherence, longevity, and translational specificity. Columbia University’s nanoparticle IP platform for peptide delivery must meet those same tests. Its commercialization infrastructure provides a concrete basis for comparison, but the patent example offered to establish its foundational priority names other applicants, leaving that central claim unresolved.
Why raw patent count is the wrong way to measure a university's nanomedicine depth
A patent total counts inventions that fit together and filings that have no links in the same way. Yet a delivery platform depends on how its claims fit together. A large portfolio may come from many laboratories working on their own or from work built on the same technology. Counting alone cannot distinguish those two structures.
Citation counts introduce another distortion because older patents have had longer to accumulate references. The broad protein and peptide therapeutics citation graph is anchored by older antibody-engineering patents, whose prominence reflects longevity. Age can support an assessment of depth, but influence in an adjacent field does not establish peptide nanoparticle expertise. The useful criteria are coherence through shared underlying technology, longevity through an established priority history, and translational specificity through claims tied to a defined therapeutic route.
Why peptide nanoparticle delivery is a hard engineering problem that rewards deep, cumulative IP
Endogenous GLP-1 has a half-life of one to two minutes. DPP-4 degrades it, while renal clearance further limits its time in the body. That short window makes protection and transport central to delivering the peptide, requiring attention before peptide chemistry is complete. What use is a promising payload if it cannot reach its intended site in a useful form?
Nanoparticle encapsulation addresses that problem by protecting the payload from degradation and modulating transport for targeting and controlled release. These functions connect chemistry, biology, and delivery engineering. Making progress takes more than a single formulation result, especially when the chosen route has its own transport constraints. Work over time can lead to inventions built around the same mechanism. Longevity tells more when the engineering builds on earlier work than when an old filing is followed by research with no link to it.
Where the global peptide nanoparticle patent landscape actually sits, and who is building it
Shandong University, China Pharmaceutical University, and Fudan University are among the active institutions in peptide drug conjugate patents, including PD-L1/PROTAC convergence subcategories. Filings entering international prosecution phases put this activity into the competitive context for US university IP. These categories are adjacent to nanoparticle-mediated peptide delivery. These categories show that inventions are coming from more parts of the world, but they do not show how all the institutions rank against one another.
Industrial assignees dominate the broader protein and peptide therapeutics landscape. MIT, Stanford, the University of Pennsylvania, and the University of California system are leading US academic filers, but occupy the 19th–29th positions overall when commercial assignees are included. Those positions describe the broad field. King’s College London offers a sign of new research through its acyl-ghrelin peptide gold nanoconjugates for nose-to-brain delivery, published in Small in September 2025 after electronic publication in July 2025. That publication shows new scientific work, but it does not show how deep the patent portfolio is or who owns the patents.
How the top US research universities compare on coherence, longevity, and translational specificity
The National Academy of Inventors’ 2025 worldwide and US-only rankings measure total US utility patents granted to universities. They provide a baseline for institutional output. MIT and Stanford have broad nanoparticle and peptide portfolios distributed across delivery modalities and disease areas. That breadth represents institutional strength. Whether that breadth adds up to a coherent platform depends on how the claims fit together, which a total for the whole institution cannot show.
The University of Pennsylvania’s strength is concentrated in lipid nanoparticle delivery, a distinct technology from peptide-specific nanoparticle systems. Its claims also overlap heavily with industrial filers, making the competitive context different from that of a narrowly defined university platform. The University of California system’s broad filing position likewise does not, by itself, resolve coherence or route specificity. These institutions cannot be ranked fairly when the evidence for each measures different things. Their portfolios address different technical problems.
Moffitt Cancer Center provides a more focused comparison. Its WO2025049877A1, published in March 2025, covers a virus-like nanoparticle platform for mRNA delivery in adaptive therapy. That is clinically motivated IP within a narrower disease setting, rather than evidence of a cross-indication peptide platform. The contrast exposes the central question for large universities. Do their filings share a delivery mechanism, or does their apparent depth arise from aggregating independent programs?
What makes Columbia University’s nanoparticle IP platform for peptide delivery different from its peers
The proposed distinction for Columbia is a long-standing delivery mechanism applied across peptides, oligonucleotides, and other payloads. But the named patent does not substantiate that attribution. WO2011019585A1 covers drug delivery using unfolding and folding proteins and peptide nanoparticles, yet its applicants are NANJING EFFECT PHARM DRUG DEVELOPMENT Corp, Nanjing University, and NanoPax Pharma LLC. It cannot establish Columbia’s foundational priority.
That discrepancy changes the comparison in a substantive way. An early document supports longevity only for the rights and applicants to which it belongs. Nor does an early date alone establish that broad claims govern later implementations. Columbia’s asserted cross-payload coherence therefore remains a proposition requiring Columbia-attributable patent evidence. The available material supports a clearer distinction in its commercialization structure than in the asserted seniority of its peptide nanoparticle claims.
The licensing examples also require careful separation. Columbia’s portal includes antisense oligonucleotides for MYC-targeted cancer therapy, described as steric-blocking ASOs targeting MYC mRNA. That is not, by itself, an oligonucleotide delivery platform. Work across several therapeutic classes likewise does not prove that they share nanoparticle IP. A rigorous comparison preserves Columbia’s relevant translational activity without converting neighboring technologies into evidence of a common patent foundation.
How Columbia Technology Ventures turns portfolio depth into translational momentum
Columbia Technology Ventures states its mission as transferring inventions from academic laboratories to the market. Columbia University holds title to intellectual property, which CTV manages through its technology transfer function. The Federal Register’s November 2024 notice also describes CTV as co-owner of the rights addressed there. That specific arrangement should not be generalized to every university patent. A coordinated office can bring rights management and commercialization into the same process.
Consolidating co-owned rights is intended to expedite development. This addresses a different obstacle from peptide degradation, but one that can also prevent a laboratory invention from advancing. A prospective licensee needs a workable route to the relevant rights. CTV’s licensing portal lists programs including safer ibogaine analogs for substance use disorders and the MYC-targeted ASOs. These listings show that licensing is active, but they do not prove clinical success or show that the programs belong to one nanoparticle platform.
The distinction is between infrastructure and outcome. Coordinated licensing can give a deep portfolio a path toward development, while fragmented rights can complicate that path. Therapeutic efficacy is independent of how those rights are held. Columbia’s institutional design is therefore relevant to translational seriousness, but it cannot substitute for claim-level evidence of platform coherence.
Why the nose-to-brain delivery route makes platform coherence especially valuable right now
Cheng et al.’s 2025 longitudinal study of individuals with type 2 diabetes associated GLP-1 receptor agonist use with reduced dementia incidence. That finding gives grounds for more research, but it does not prove that the drugs treat dementia. The clinical evidence poses a harder question. A meta-analysis of 15 randomized controlled trials found no improvement in memory and cognition in Alzheimer’s disease compared with placebo. Insufficient brain penetration by systemic formulations has been proposed as part of the explanation, but it has not been shown to account for every negative result.
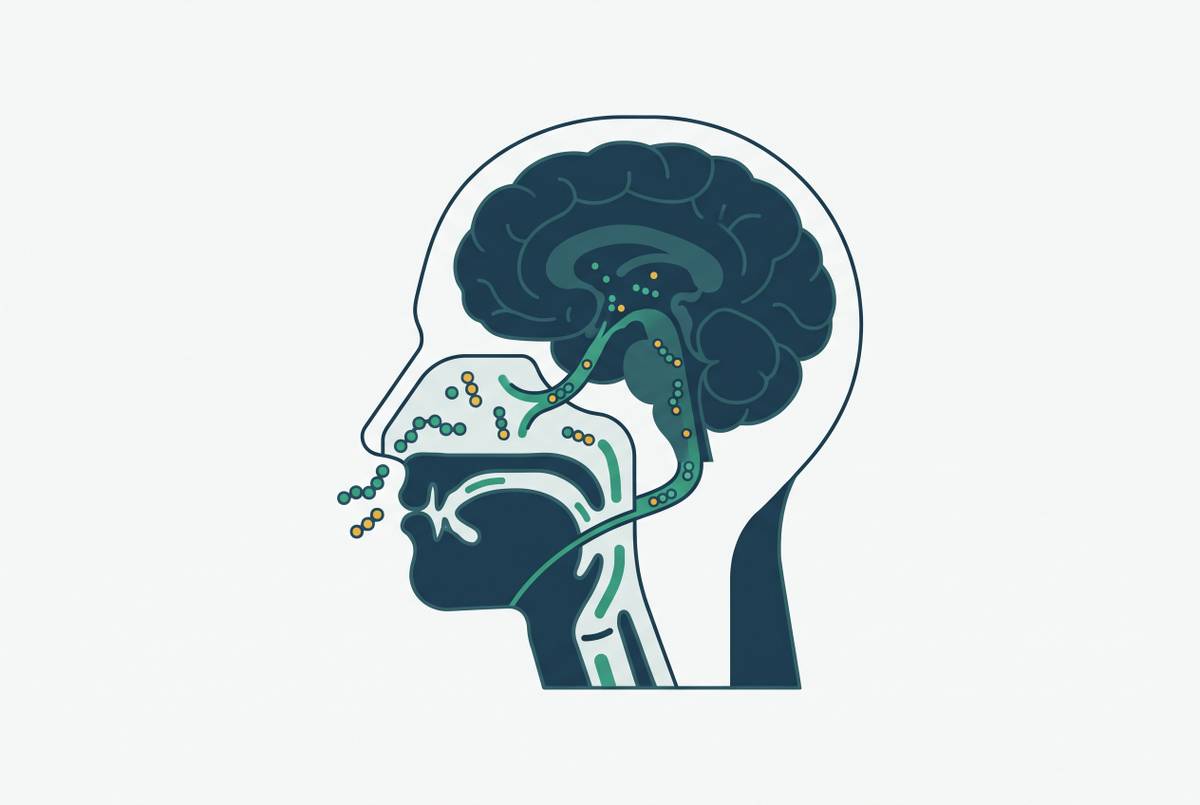
Intranasal delivery addresses that particular transport problem through the olfactory and trigeminal pathways, bypassing the blood-brain barrier and avoiding hepatic first-pass metabolism. Its potential compliance advantage over subcutaneous injection adds a practical reason to study it. Yet peptides remain vulnerable when the route changes. Nanoparticle carriers protect the payload in the nasal environment and modulate transport along those pathways, connecting protection and targeting within one delivery system.
The King’s work shows scientific activity at precisely this intersection. It does not establish that every neurological peptide needs the same formulation or that intranasal treatment will succeed. The conditional logic is nevertheless strong. If too little of a promising peptide reaches the brain, the therapeutic hypothesis must also cover how to deliver it there. Nose-to-brain nanoparticle research is then a scientifically motivated response to the exposure gap.
Why the neurological and addiction frontiers are where peptide nanoparticle IP becomes most differentiated
GLP-1 receptors are present on neuronal populations in the brain. Their presence supports investigation of receptor agonists in dementia, Parkinson’s disease, and substance use disorder, while leaving efficacy to be established for each indication. These frontiers sharpen the distinction between payload chemistry and delivery capability. A portfolio optimized for peripheral delivery does not automatically answer questions about brain exposure. A formulation aimed at the brain still needs evidence that the exposure it achieves helps patients.
Christian Hendershot’s first clinical trial of semaglutide in people with alcohol-use disorder, published in 2025, found reduced alcohol craving and episodes of heavy drinking, providing an early clinical signal. Baseline Therapeutics in San Francisco is developing BT-001, a GLP-1 mimic for alcohol-use disorder, and its Phase III trials launched in 2026. That program shows the indication moving toward clinical scale, but it does not validate nanoparticle delivery or establish that systemic administration cannot work. Brain penetration remains to be investigated through engineering.
CTV’s safer ibogaine analog program places Columbia’s licensing activity in the same addiction-neuroscience territory, though the compounds belong to a distinct therapeutic class. This is evidence of institutional engagement with the indication. It is not evidence that those compounds share a GLP-1 delivery platform. The differentiated patent position would arise where coherent claims address the specific transport requirements of neurological therapy, rather than merely mentioning an attractive disease area.
What translational seriousness actually looks like across a university peptide nanoparticle portfolio
Translational seriousness shows when the patent structure and the way rights are managed fit the needs of the therapy. Columbia serves as a useful case because its coordinated licensing apparatus is concrete, while the supplied foundational patent attribution exposes the limits of the platform claim. Both observations belong in the assessment. An institution can have a credible commercialization function without the available evidence establishing the claimed depth of a particular delivery portfolio.
Roughly half of patients discontinue GLP-1 therapy within a year, with GI side effects as the primary driver. Pooled study data show that patients stay on treatment longer with oral delivery than injectable delivery, a benchmark that intranasal approaches must eventually match or beat. An alternative route is therefore not valuable simply because it is different. Its case for clinical and commercial use depends on solving a documented problem, without assuming that a change in delivery will remove adverse effects.
For clinicians, investors, and scientific peers, the practical assessment begins with three questions. Do the claims share underlying technology that ties them into a coherent platform? How long has that foundation existed, as shown by attributable priority dates? Do the claims map onto a defined disease and delivery route where transport limits treatment?