GLP-1 Injection Site Reactions and Subcutaneous Tissue Effects
The biology of depot formation, not manufacturing flaws, explains why injection sites react.
The subject here is straightforward: GLP-1 medications have to sit in subcutaneous tissue for days at a time to work, and that requirement, not some manufacturing flaw, is what produces the redness, the nodules, and eventually the scar tissue that shows up at injection sites. Understanding the biology behind these reactions explains why they happen at all, and why, for a drug class patients are expected to take for years, they add up to something more than a footnote in the prescribing information.
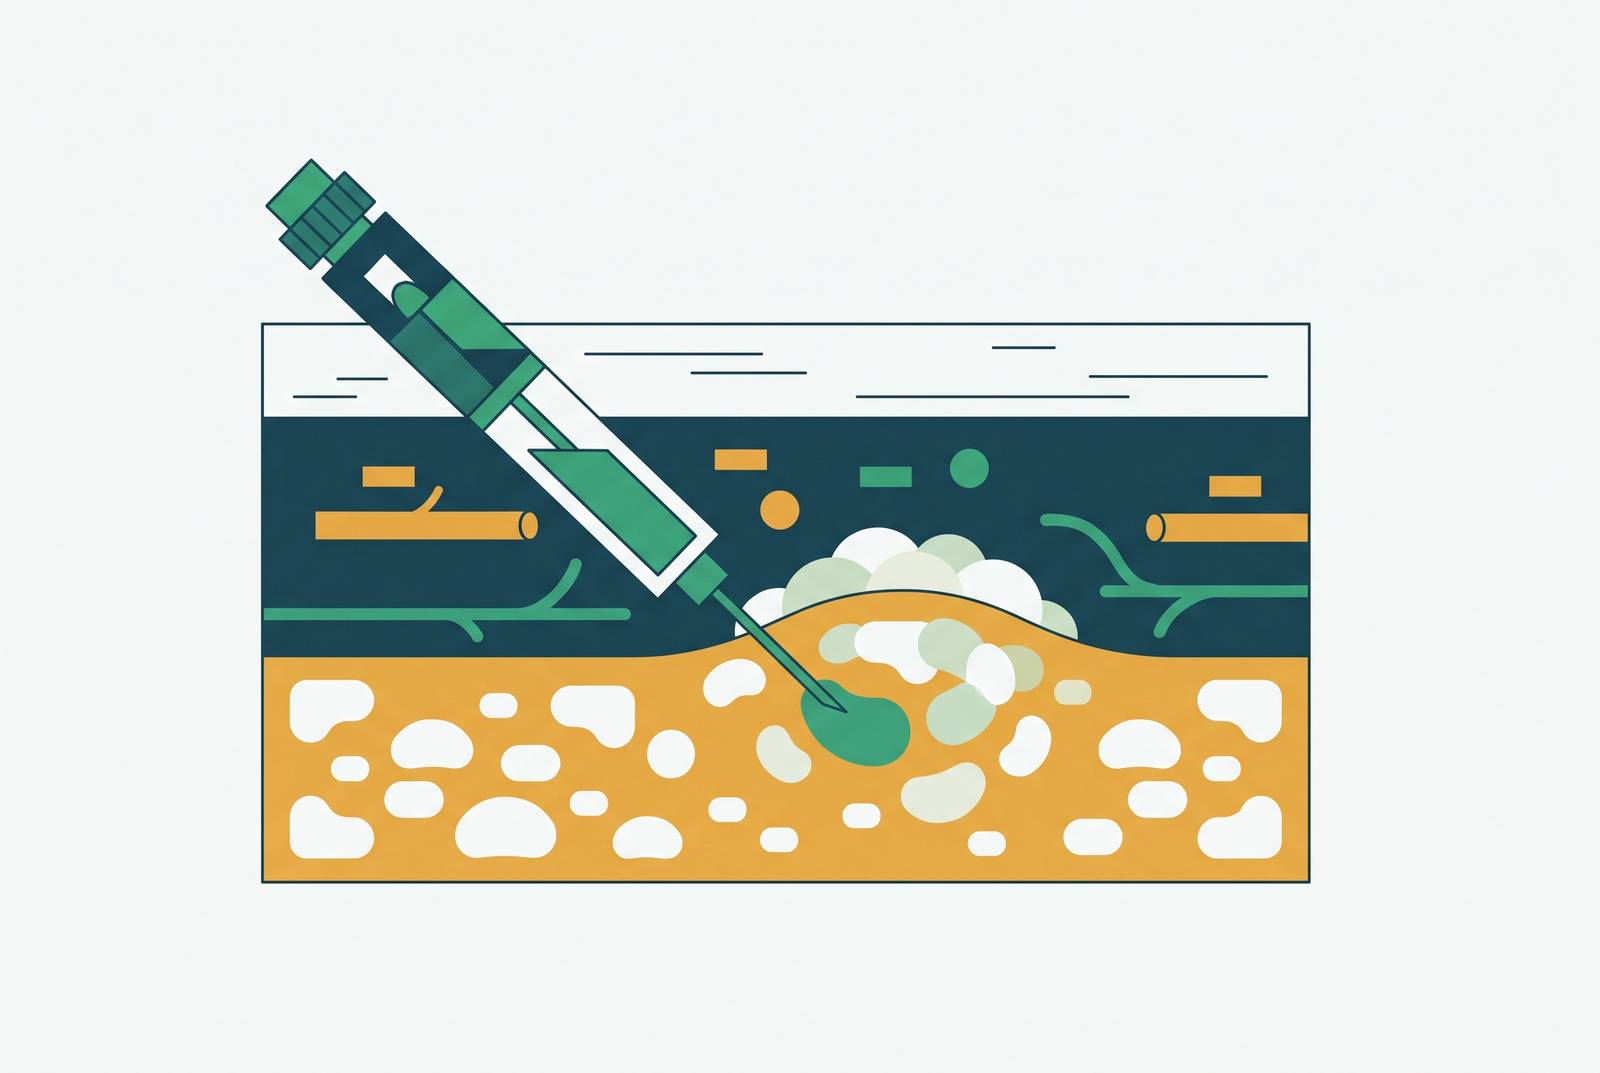
Native GLP-1, the hormone the body makes on its own, is a short peptide that lasts under two minutes in circulation before enzymes break it down. That's not long enough to do anything useful as a once-weekly injection, so the engineered versions on the market (liraglutide, semaglutide, tirzepatide, exenatide, dulaglutide) solve the stability problem by binding to albumin, resisting enzymatic breakdown, or forming a slow-release depot right under the skin. The depot is the whole point. It is the mechanism that makes weekly or daily dosing possible in the first place, not a side effect of formulation. But asking a patch of tissue to hold and slowly release a foreign peptide, week after week, means asking that tissue to also handle everything that comes with it, including the local immune response, the nerve irritation, and the physical presence of a growing depot that has to break down before the next one arrives.
What the tissue actually experiences: the spectrum from acute reaction to chronic remodeling
Subcutaneous fat is a metabolically active tissue. It's full of capillaries, nerve endings, and mast cells that exist specifically to detect and respond to things that don't belong there, plus adipocytes that turn out to have their own relationship with GLP-1 signaling. So when a needle delivers a depot of drug into that space, several things happen almost immediately, and a few more happen over months and years.
The earliest reactions show up within a day or two and usually clear within a week. Stinging during the injection itself comes from a mismatch between the formulation's pH, generally neutral to slightly alkaline, and the tissue it's entering. Because most formulations are reasonably close to the body's own pH, the irritation tends to be brief. Redness follows from local capillaries dilating as part of the inflammatory response, and it typically fades within 24 to 48 hours, occasionally stretching to a week. Itching, or pruritus, shows up more often than any other injection-site symptom across GLP-1 trials, and it's more common with sustained-release products than with solution-based ones. Bruising is different in kind: it comes from the needle nicking small vessels, not from anything pharmacological, and it hits harder in patients on blood thinners.
A step up from that sits a set of subacute reactions: localized swelling that has some firmness to it, meaning the inflammation hasn't fully resolved into simple redness, and outright nodules. Nodules are the most formulation-dependent reaction in the entire category. Extended-release exenatide, which uses PLGA microspheres roughly 50 microns across to achieve its release profile, produced injection-site nodules in around one in ten patients in the DURATION-6 trial (Jones et al., 2015), and the mechanism is almost mechanical: the microspheres sit in the tissue and degrade slowly, and the body walls them off in the meantime. Solution-based agents like semaglutide and tirzepatide don't carry that same microsphere architecture, so their nodules tend to be rarer and shorter-lived.
What happens after months or years of repeated injections into overlapping territory is a separate matter. Lipohypertrophy (thickened, firm patches of fat under the skin) involves fat piling up alongside structural changes in the tissue. It's scar-like tissue remodeling, the same category of change seen in insulin users who reuse injection sites, and it changes how the tissue behaves going forward. Inject into lipohypertrophic tissue and absorption becomes unpredictable: sometimes slower, sometimes faster, which means the drug's effect on blood sugar or appetite gets noisier right when consistency matters most. Scar tissue from accumulated inflammation also tends to make later injections more painful, which is its own quiet driver of avoidance.
One thread worth pulling on further: GLP-1 receptors exist directly in adipose tissue, and the effects there may run through the canonical GLP-1 receptor or through a separate growth-factor receptor pathway, not just through systemic appetite suppression. That would help explain something clinicians have noticed anecdotally, that facial fat loss in patients on these drugs seems to exceed what overall body weight loss would predict. It raises the possibility that some of what's happening is local to specific fat depots, not just a downstream effect of eating less. And on the far end of the spectrum sit the rare but serious reactions, delayed hypersensitivity, spreading cellulitis, abscess, that aren't typical but are part of the honest clinical picture and warrant a call to a doctor, not a shrug.
How often these reactions actually occur, and why the numbers are harder to pin down than they look
Pinning an exact number on injection site reactions turns out to be harder than it looks, mostly because the number depends heavily on which drug, which formulation, and which data source you're looking at. Clinical trials put the range across a wide span of patients, but that spread is wide enough to be almost meaningless on its own.
Formulation explains most of the spread. Filippatos et al. found injection site reaction rates of 5.1% for twice-daily exenatide, 16% for the once-weekly version, 3.9% for lixisenatide, and 15% for albiglutide, with semaglutide sitting near the low end of the whole distribution. A crossover trial by Snitker et al., with 104 patients, put a number on the pain difference directly: semaglutide scored 5.6 mm on a 100-mm pain scale versus 11.5 mm for dulaglutide. Both fall well within "mild," but the gap between them was statistically real, not noise.
A 2026 meta-analysis by Taj et al., pooling 14 randomized trials covering 4,861 patients and 396 injection site events, found a risk ratio of 3.55 (95% CI 2.35 to 5.36) for GLP-1 receptor agonists compared to control groups. In plain terms, users of these drugs faced more than triple the injection site reaction risk of people not on them. That's a meaningful signal, even before factoring in how it plays out once the drugs leave the tightly monitored world of a clinical trial.
FAERS, the FDA's adverse event reporting system, tells a rougher and noisier story once the drugs hit the general population. Between the second quarter of 2022 and the first quarter of 2024, tirzepatide alone generated 37,827 adverse event reports, with injection site pain and hemorrhage both landing in the top five most-reported categories. In 2024 specifically, 5,273 of those reports were injection site pain, concentrated most heavily in women between 40 and 59 (Almansour et al., 2025). It's worth being careful with what that number actually means: FAERS counts raw reports, not a percentage of users affected, so as prescriptions climbed, so did the raw count, almost mechanically. The actual share of tirzepatide users affected likely sits closer to the 3-5% range seen in trials.
Still, the broader dermatologic picture deserves attention on its own terms. The same 2026 Taj et al. analysis found that dermatologic adverse events made up 6.08% of all GLP-1 related adverse events reported to the FDA through January 2024, a total of 4,896 out of 80,482 reports, a category that tends to get less scrutiny than the gastrointestinal side effects that dominate the conversation. That analysis also flagged specific disproportionality signals: exenatide showed up strongly associated with injection-site hemorrhage (a proportional reporting ratio of 27.6), and dulaglutide showed a similar pattern (PRR of 11.5). The gap between clean trial numbers and messy real-world reporting isn't a contradiction, it's information. Trials use trained injectors, monitored rotation schedules, and close follow-up. Real patients, injecting themselves at home for years, don't have any of that scaffolding.
How cumulative tissue damage from repeated injections compounds over time
A single injection reaction is, on its own, a minor and temporary event. The complication is that GLP-1 therapy isn't a short course of treatment. Weight tends to return once patients stop (a pattern the next section returns to), which means the injection burden continues indefinitely rather than something patients work through and finish. It's ongoing, often for years.
At a weekly cadence, each injection site takes in a new depot roughly every seven days. If rotation isn't thorough, or if a patient defaults to the same easy patch of abdomen out of habit, tissue doesn't get a full chance to recover before the next dose lands. The mechanism compounds in a fairly linear way: an injection into tissue that's still mildly inflamed from the last one triggers a new inflammatory cascade stacked on top of the old, unresolved one. Do that enough times and fibroblasts activate, collagen builds up, and the tissue starts down the path toward the kind of scar-like remodeling described earlier as lipohypertrophy. Once that tissue changes, its blood supply and absorption behavior change with it, so injecting into it introduces exactly the kind of pharmacokinetic variability that can quietly undermine glycemic control or weight-loss results, without the patient necessarily connecting the dots.
Some patients face a sharper version of this problem than others. People with generalized lipodystrophy, a condition marked by a near-total lack of subcutaneous fat, find subcutaneous injections, GLP-1 or otherwise, especially painful and technically difficult. There simply isn't much tissue available to absorb a depot gracefully. Patients with eczema, dermatitis, or autoimmune skin conditions tend toward more severe or longer-lasting reactions even when doing everything correctly, and patients on anticoagulants face amplified bruising and hemorrhage risk at every single injection, not just occasionally.
Dose escalation adds another layer. Higher doses mean a bigger depot and a stronger local inflammatory signal, not just a stronger systemic effect. The 2025 STEP UP trial, testing an investigational 7.2 mg dose of semaglutide, found gastrointestinal adverse events in about 71% of participants, compared with 61% at the standard 2.4 mg dose and 43% on placebo. As doses climb in pursuit of greater weight loss, local and systemic burden rise together, not independently. That's the structural bind at the center of this entire discussion: the tissue is simultaneously the delivery site and the thing being damaged by delivery, and no amount of careful technique fully separates those two roles.
Why injection site reactions translate into real discontinuation, even when clinical trials suggest otherwise
Clinical trials consistently show that injection site reactions rarely cause patients to quit outright. That finding is real, but it says more about trial conditions, trained staff, close monitoring, financial and social incentives to stick with the protocol, than it does about what happens once patients are managing the drug alone at home.
Real-world persistence tells a much less reassuring story. One-year persistence estimates land somewhere between 32% and 50%, with the proportion of days covered by an active prescription averaging only 51% to 54%. Looking at obesity-indicated high-potency GLP-1 products by the year patients started: persistence sat at 33.2% in 2021, 34.1% in 2022, 40.4% in 2023, and 62.6% in 2024. That 2024 jump is worth treating with some caution. It probably reflects easing supply shortages more than any shift in how patients actually tolerate the drugs. A population-based study of semaglutide discontinuation in Denmark found that more than half of users had stopped within a year. And a Polish database (LUX MED) found only 6.6% reached long-term use, defined as 12 or more consecutive prescriptions, while 35.1% filled just a single prescription and never returned.
Patients who'd previously taken gastrointestinal medications, a rough proxy for having already experienced some adverse effect from an anti-obesity drug, were 9% more likely to stop within the first year. And the timing of dropout is itself a clue: discontinuation tends to peak during dose escalation, a phase when systemic side effects are also most pronounced. That pattern points toward the body's actual experience of the drug as a driver of quitting, not just cost or simple forgetfulness, though cost is hardly a minor factor either. Annual gross costs for these medications exceeded $12,000 per patient in 2025, and out-of-pocket prices for even the lowest dose of semaglutide ran around €2,000 as of June 2025. A patient paying that much out of pocket while also dealing with sore, lumpy injection sites has every reason to weigh the whole experience harshly.
What makes all of this matter clinically, and not just as a comfort issue, is what happens after people stop. Persistent patients saw a 10.9% weight change at 12 months, while those who discontinued saw just 2.2%. These are, in practical terms, lifelong medications for most patients who benefit from them, which means the ongoing injection burden and the tissue damage it accumulates aren't a minor footnote. They're a central part of whether the treatment actually works over years, not just over a single clinical trial.
What site rotation and injection technique can and cannot fix
Standard guidance recommends rotating between the abdomen, the upper thigh, and the upper arm, the three approved injection zones, and rotating within each zone as well, not just between them. Because GLP-1 dosing is weekly rather than daily, patients actually have more room to plan rotation carefully than someone managing daily insulin injections does; each patch of tissue gets a longer stretch of recovery time before it's asked to absorb another depot.
The practical version of this is almost embarrassingly simple. Divide the abdomen into quadrants and move clockwise each week. Keep a note, on paper or in a phone app, of where the last few injections went, so the same spot doesn't get hit out of habit. Overusing one site is what leads to scar tissue, reduced absorption, and lingering inflammation, and nearly all of that is avoidable with a bit of planning. Letting the pen warm to room temperature for 15 to 30 minutes before injecting cuts down on the vasoconstriction-then-rebound cycle that makes cold medication sting more, and pushing the plunger slowly rather than quickly reduces the physical trauma to the tissue itself.
But technique has limits, and they're worth being honest about. The pH mismatch between the formulation and the subcutaneous environment doesn't go away because the injection was administered carefully; it's a property of the drug and the tissue, not the technique. The sustained-release depot that makes once-weekly dosing possible in the first place is the same property that keeps the drug sitting in the tissue for days, and no injection technique shortens that residence time. Nodule formation tied to microsphere-based formulations, extended-release exenatide being the clearest example, is architectural, baked into how the drug is built. Patients with generalized lipodystrophy simply don't have enough subcutaneous tissue to rotate into in the first place, no matter how disciplined their technique is. And even for patients with plenty of tissue to work with, years of accumulated scar tissue slowly shrink the amount of usable, healthy real estate available for rotation.
The honest summary is that technique reduces both the frequency and the severity of these reactions. It doesn't eliminate them, and it doesn't stop the slow remodeling that happens in long-term users no matter how carefully they rotate. Good technique manages a symptom. It doesn't touch the underlying mismatch between what these drugs need to do (sit in the tissue and release slowly) and what that tissue experiences as a result.
Why eliminating subcutaneous delivery is the only way to eliminate subcutaneous tissue reactions
Follow the logic through every section above and one conclusion keeps presenting itself: the reactions described here, from the stinging on injection to the nodules to the years-long slide into lipohypertrophy, aren't accidents of poor technique or unlucky patients. They're the direct, predictable output of putting a large peptide depot into subcutaneous fat again and again. The tissue does exactly what tissue does when it encounters a foreign, slow-releasing substance week after week: it inflames, it responds, and eventually it remodels. Rotation and technique can soften that response, but they can't remove the depot from the tissue, because the depot in the tissue is the treatment.
That points toward one direction as the only one capable of fully resolving the problem rather than managing it: routes of delivery that don't rely on a subcutaneous depot at all. Oral GLP-1 formulations represent one such approach already reaching patients, built to survive the stomach and get the peptide into circulation without ever asking subcutaneous fat to hold a slow-release reservoir. Whatever tradeoffs that route carries (bioavailability challenges, dosing complexity, absorption variability with food), it sidesteps the specific mechanism this piece has traced from the molecular level to the epidemiological one: a needle depositing a pH-mismatched, long-residence depot into the same limited patch of fat, week after week, for years. Subcutaneous tissue reactions have one root cause. The only way to remove them completely is to stop asking that tissue to do the job in the first place.
Sources
- Tirzepatide Injection Site Reactions: Causes & Relief
- Injection‐site and dermatologic reactions associated with glucagon‐like peptide‐1 receptor agonists: Insights from meta‐analysis of randomised controlled trials and real‐world evidence - Taj - 2026 - Diabetes, Obesity and Metabolism - Wiley Online Library
- Injection‐site and dermatologic reactions associated with glucagon‐like peptide‐1 receptor agonists: Insights from meta‐analysis of randomised controlled trials and real‐world evidence
- GLP-1 Injection Site Reactions: Causes and Fixes | RethinkPeptides
- A Closer Look at the Dermatological Profile of GLP-1 Agonists
- Tirzepatide-Induced Injection Site Reaction
- Glucagon‐like peptide‐1 elicits vasodilation in adipose tissue and skeletal muscle in healthy men
- healio.com